Acute Coronary Syndrome (ACS) (Guidelines)

Warning

Audience

  • North NHS Highland
  • Primary and Secondary Care
  • Adults only
  • This is the combined pathway for both Raigmore and Rural use.
For the Emergency Department Acute Coronary Syndrome (ACS) pathway booklet, which incorporates the above guidance, click here: Emergency Department home page.
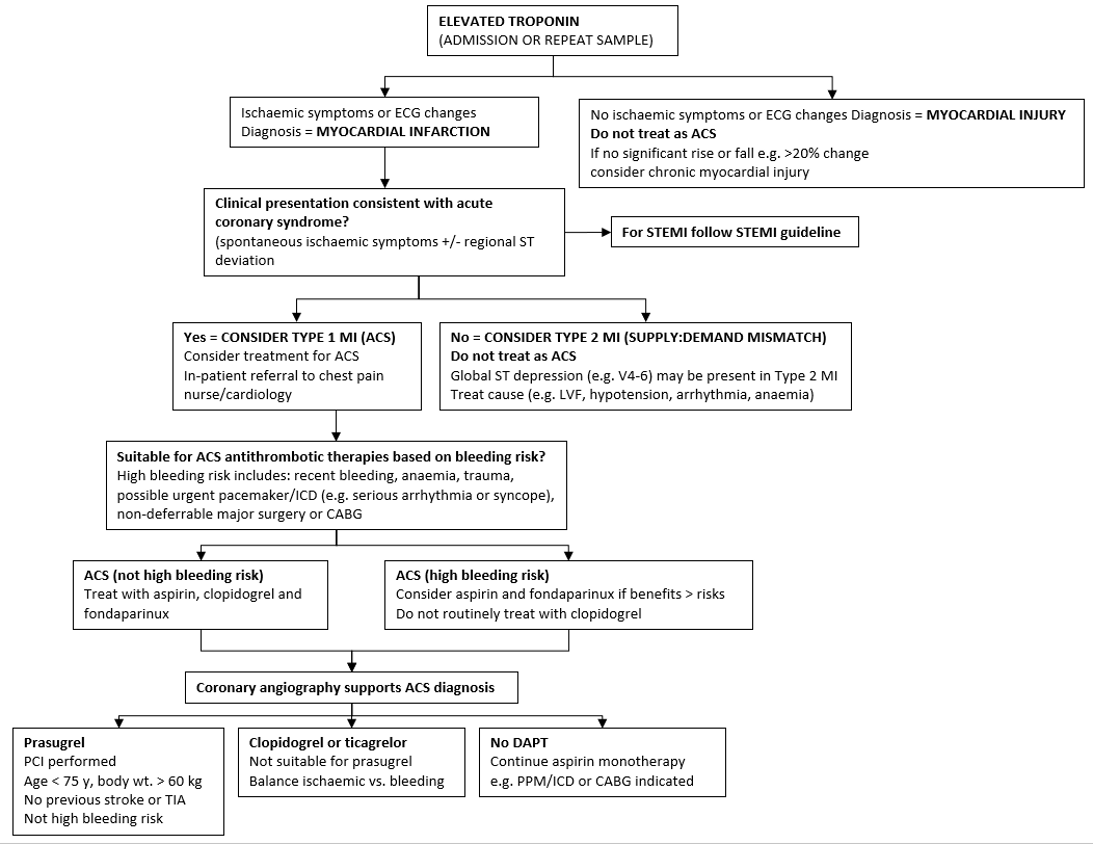
Part 1 Acute coronary syndrome

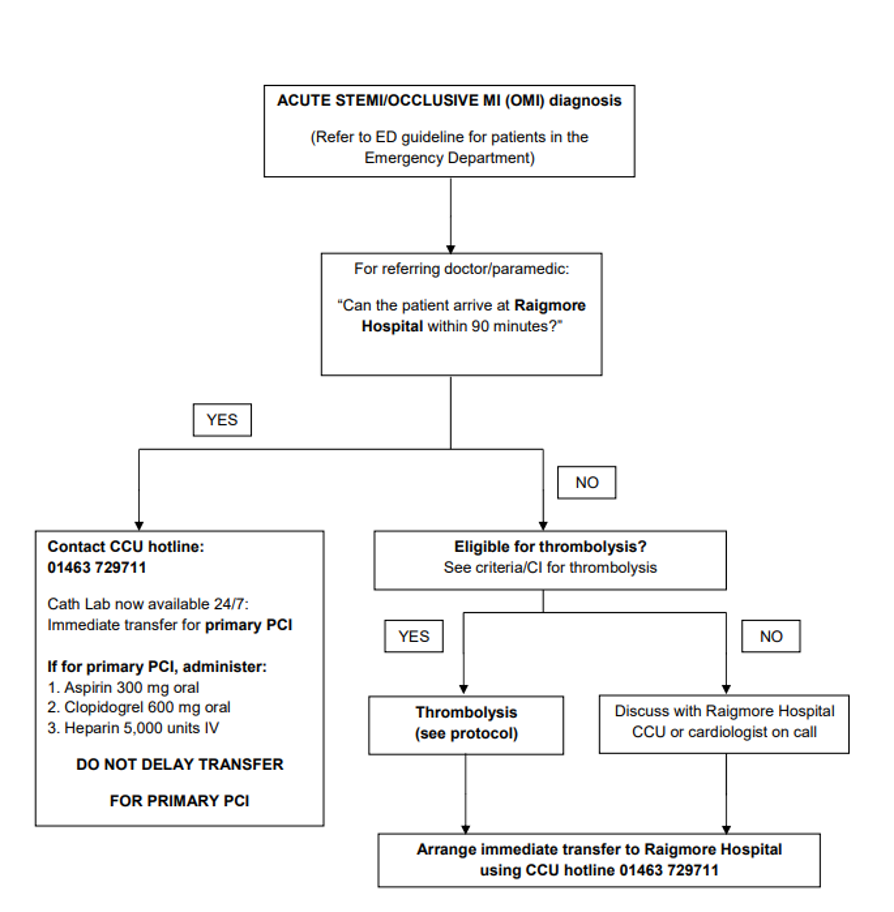
Part 2 Acute coronary syndrome


For the Emergency Department Acute Coronary Syndrome (ACS) pathway booklet, which incorporates the above guidance, click here: Emergency Department home page.

Criteria for thrombolysis

For a printable form, click here: Criteria for thrombolysis form (NHS Highland intranet access required). 

Thrombolysis administration

Drug administration for tenecteplase thrombolysis  Age under 75 years  Age 75 years or older 
Step 1 Aspirin 300mg oral (ideally soluble or chewed), if not already given  Aspirin 300mg oral (ideally soluble or chewed), if not already given 
Step 2 Tenecteplase (TNK) full dose 0.5mg per kg IV (see below) Tenecteplase (TNK) half dose 0.25mg per kg IV (see below)
Step 3 Unfractionated heparin (UFH) 4000 units IV bolus  No UFH bolus 
Step 4 Clopidogrel 300mg oral Clopidogrel 75mg oral 
Step 5  Enoxaparin 1mg/kg bd s.c. (max 100mg per injection for the first two doses)  Enoxaparin 0.75mg/kg bd s.c. (max 75mg per injection for the first two doses) 

Special considerations:

  • If enoxaparin is unavailable and long or delayed transfer, consider UFH 1000 unit i.v. bolus after 2 hours
  • If eGFR <30, regardless of age, the enoxaparin s.c. doses are given once daily
  • If eGFR <15, enoxaparin is not recommended, UFH IV infusion is preferred with aPTT monitoring
  • If patient is taking warfarin, check INR immediately and omit UFH/enoxaparin until INR <2
  • If patient is taking DOAC (e.g. edoxaban), omit UFH/enoxaparin until >12hours since last DOAC dose
  • If fondaparinux has already been given, administer UFH IV bolus if age <75yrs, omit enoxaparin for 24 hours
  • If tenecteplase is unavailable, it can be substituted by alteplase (requires infusion pump, no half-dosing)

Tenecteplase (TNK) dosing regimen


Age <75 yrs

Age ≥75 yrs

Weight (kg)

TNK (units)

TNK (mg)

Vol (mL)

TNK (units)

TNK (mg)

Vol (mL)

< 60

6,000

30

6

3,000

15

3

60 - < 70

7,000

35

7

3,500

17.5

3.5

70 - < 80

8,000

40

8

4,000

20

4

80 - < 90

9,000

45

9

4,500

22.5

4.5

≥ 90

10,000

50

10

5,000

25

5

Unfractionated heparin IV infusion (only if eGFR <15)
Following IV UFH bolus, start IV UFH infusion of 12 units per kg, up to a maximum of 1,000 units/h for 24 to 48 hours.
Target aPTT: 50 to 70 s, or 1.5 to 2.0 times control at 3, 6, 12 and 24 h

Early rule out pathway for Acute MI

TAM135 ACS Raigmore flowchart


TAM135 ACS Rural flowchart


Troponin-ACS refresher

Abbreviations

  • GTN: Glyceryl trinitrate
  • ECG: Electrocardiogram
  • CCU: Coronary care unit
  • Hs-cTnl: high-sensitivity cardiac troponin
  • STEMIST:-Elevation Myocardial Infarction
  • AV: Atrioventricular block
  • SBP: Systolic blood pressure
  • DBP: Diastolic blood pressure
  • LBBB: Left bundle branch block
  • eGFR: Estimated glomerular filtration rate
  • DOAC: Direct oral anticoagulants
  • UFH: Unfractionated heparin
  • aPTT: Activated partial thromboplastin time
  • PCI: Percutaneous Coronary Intervention 

Editorial Information

Last reviewed: 20/01/2025

Next review date: 20/01/2028

Author(s): Cardiology .

Version: 10.1

Approved By: TAM subgroup of the ADTC

Reviewer name(s): Dr J Watt, Consultant Cardiologist .

Document Id: TAM135

Related resources

Further information for Health Care Professionals

(Scroll down to see all references)

References

Further information for Patients

Self-management information