TAM (Treatments and Medicines) NHS Highland

Acute Coronary Syndrome (ACS) (Guidelines)

Warning
What's new / Latest updates
25/09/26 V10.1: Flowcharts reformatted no clinical changes, ng changed to nanogram throughout.
11/09/26: Early rule out pathway for acute MI for Raigmore and Rural hospitals added, showing new second troponin pathway
09/07/26:
Criteria for thrombolysis -
- 'LBBB with STEMI equivalent' changed to 'LBBB with ≥ 1 positive Smith-modified Sgarbossa criteria (discuss with CCU)'
Ischaemic symptoms -
- Removed wording 'posterior MI'
- Added: Left bundle branch block with occlusive MI changes defined by ≥ 1 of 3 Smith-modified Sgarbossa criteria:
- concordant ST elevation ≥ 1 mm
- concordant ST depression ≥ 1 mm in V1 - V3
- discordant STE ≥ 25% depth of preceding S-wave (https://litfl.com/sgarbossa-criteria-ecg-library/)
20/01/25
- Guideline reviewed. No amendment
22.11.23 Update
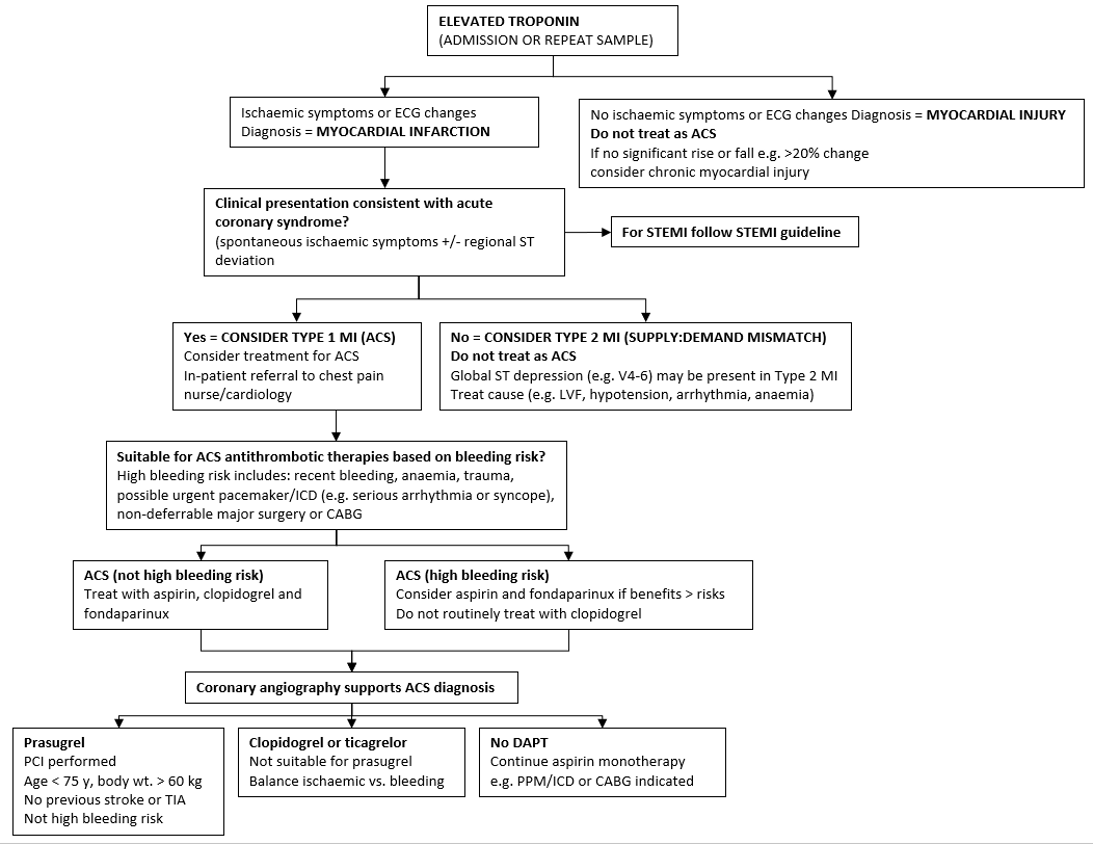
- New troponin assay and Early Rule Out of MI pathway
06.10.23 Update on the new parts for ACS pathway
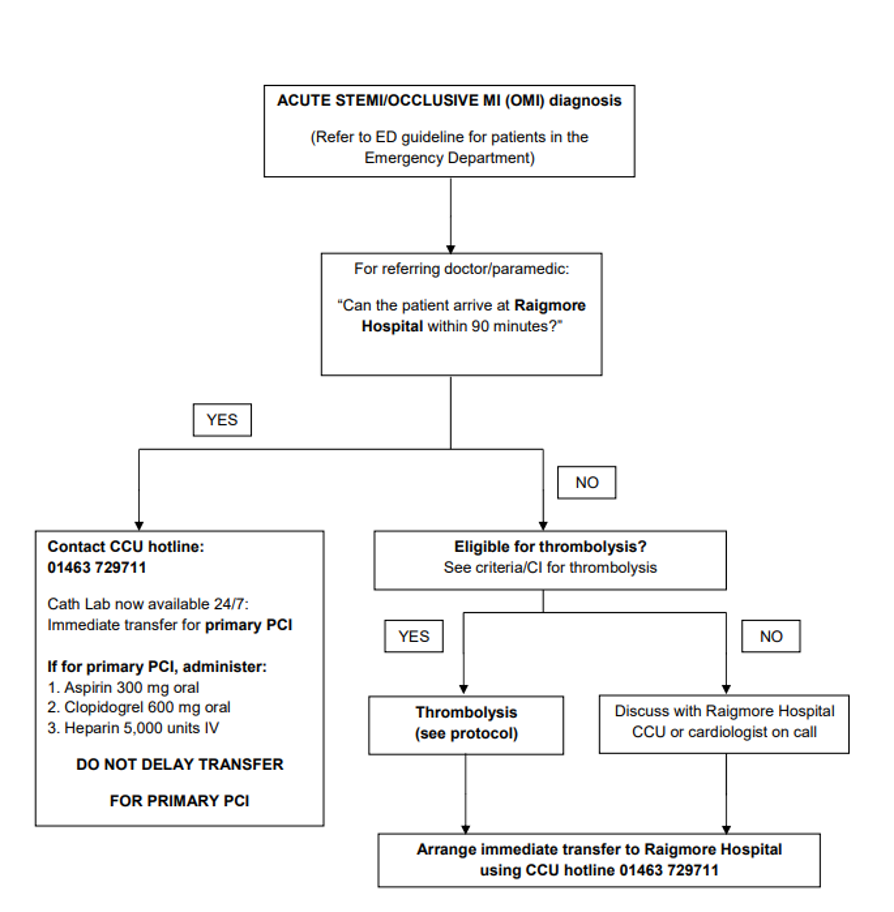
- Now UFH 5000 units to primary PCI
- 24/7 PCI now available in Raigmore, simplifies STEMI pathway
- The ECG criteria for STEMI/OMI have been subtly modified to improve diagnostic performance
Audience
- North NHS Highland
- Primary and Secondary Care
- Adults only
- This is the combined pathway for both Raigmore and Rural use.
For the Emergency Department Acute Coronary Syndrome (ACS) pathway booklets, see the links below
**note different pathways for Raigmore Hospital and Rural General Hospitals (RGH) due to differing assays in use**
RAIGMORE ED - Chest Pain ACS pathway
RGH - Chest Pain ACS pathway
For the Emergency Department Acute Coronary Syndrome (ACS) pathway booklet, which incorporates the above guidance, click here: Emergency Department home page.

For a printable form, click here: Criteria for thrombolysis form (NHS Highland intranet access required).